If you’ve ever sat in on a minimally invasive gynaecological or urological surgery, you’ve probably heard it before: the low, steady hum of a surgical power system cutting through tissue with pinpoint precision. As a supplier of these systems, I get asked this question more than any other, and for good reason. Cutting speed isn’t just a number—it’s the fine line between a procedure that goes smoothly and one that hits unforeseen snags, between optimal patient outcomes and avoidable complications. Let’s break this down, not with jargon that leaves you glossing over paragraphs, but with the practical, on-the-ground context that comes from working in this field day in and day out. Gynaecology and Urology Surgical Power Systems
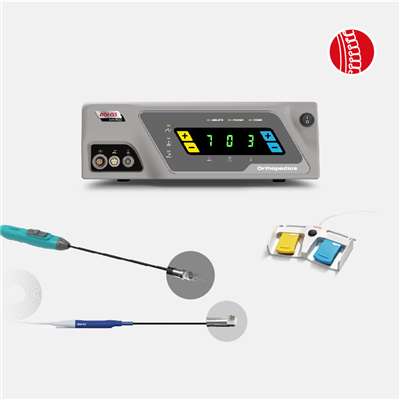
First, let’s get one thing straight: there’s no single “magic cutting speed” for gynaecology and urology surgical power systems. The speed is never universal—it’s calibrated to the specific tissue you’re working on, the type of procedure, and even the patient’s unique anatomy. When I’m with a surgeon in the OR (operating room), I see them adjust dials and toggle settings in seconds, not because they’re guessing, but because they’re making split-second calls based on what they’re cutting through.
Let’s start with gynaecological applications, since that’s half our focus. The tissues here range from soft, delicate uterine lining (endometrium) to thicker, fibrous uterine fibroids, and even the tough cervical tissue in procedures like a loop electrosurgical excision procedure (LEEP) or a hysterectomy. For soft, friable tissue—like the lining of the uterus during an endometrial ablation—surgeons typically use lower rotational cutting speeds, usually between 500 and 1,500 RPM (revolutions per minute). At this speed, the blade or resectoscope loop glides through tissue without generating excessive heat, which is critical to avoid damaging nearby healthy organs like the bladder or ovaries. I’ve seen what happens when speed is too high here: unintended thermal injury that can lead to post-op pain, bleeding, or even fistulas in some cases. It’s not worth the risk, so lower, controlled speed is standard for gentle gynaecological work.
Now, move to denser gynaecological tissue, like uterine fibroids. Fibroids are tough, often woody masses that don’t cut like natural tissue. For myomectomies (procedures to remove fibroids), rotational speeds jump to 1,500 to 4,000 RPM. This higher speed gives the cutting tool enough torque to bite into the dense fibroid without stalling or tearing. When a tool stalls mid-cut, the surgeon has to apply more force, which can lead to accidental tearing of the uterine wall—a serious complication. I remember one case early in my career where a surgeon was using a system with an incorrectly calibrated speed for a large fibroid; they had to pause 10 minutes into the procedure because the tool was bouncing off the tissue instead of cutting it. We swapped to a system with adjustable speed settings, and that procedure finished 15 minutes ahead of schedule, with zero complications. That’s the difference the right cutting speed makes.
Urology is where things get even more specific, because the tissues here are not just varied—they’re part of some of the body’s smallest, most sensitive structures. Let’s take transurethral resection of the prostate (TURP), one of the most common urological procedures, where surgeons remove excess prostate tissue blocking the urethra. For TURP, the standard cutting speed for the resectoscope loop is between 200 and 800 RPM. Why so low? The urethra is a narrow passage, and the prostate sits right next to the bladder and the nerves that control urinary and sexual function. Too much speed here, and you risk cutting through the urethra or damaging those critical nerves. I’ve worked with urologists who swear by this lower range because it gives them full control, even when working in tight quarters inside the bladder.
Then there’s nephrectomy (removing a kidney) or partial nephrectomy (removing a tumor from the kidney). These are open or laparoscopic procedures, where surgeons work on larger, thicker tissue. For cutting renal parenchyma (the functional tissue of the kidney), rotational speeds for ultrasonic or electric cutting instruments typically hit 3,000 to 6,000 RPM. Wait—ultrasonic? That’s a different type of power system, right? Yes, and it’s worth noting because urology relies heavily on both rotary (electric) and ultrasonic systems. Ultrasonic cutting uses vibration rather than rotation, with power levels that translate to cutting speeds measured in amplitude (how far the tip moves) rather than RPM. For ultrasonic systems used in urology, the amplitude for cutting kidney tissue is usually 50 to 100 micrometers—fine enough to avoid damaging blood vessels while still cutting through dense tissue.
Another key point: cutting speed isn’t just about rotation or vibration. It’s also tied to mode—cutting vs. coagulation. Surgical power systems often have dual modes, where the same tool can cut (high speed, low heat) or coagulate (lower speed, higher heat) to seal blood vessels. For example, during a laparoscopic hysterectomy (a common minimally invasive gynaecological procedure), surgeons will use a cutting speed of around 2,500 RPM to separate the uterine ligaments, then switch to a lower, coagulation mode to seal small blood vessels. This on-the-fly adjustment is why modern surgical power systems are so valuable—they let surgeons match speed to every part of the procedure.
Now, I know what some of you are thinking: why can’t we just have one speed that works for everything? The answer is simple: anatomy is not one-size-fits-all. A 25-year-old patient with small, soft fibroids has different tissue density than a 65-year-old patient with large, calcified fibroids. A patient with a small prostate has different urethral anatomy than a patient with an enlarged prostate. Even the tools matter— a 5mm resectoscope has different cutting requirements than a 10mm ultrasonic shear. As a supplier, I work closely with surgeons to test systems on their specific cases, adjusting speed settings to fit their preferences and the patient’s needs. Last year, I accompanied a urologist in a case where a patient had a rare, horseshoe kidney—unusually shaped, with extra tissue that made cutting tricky. We adjusted the ultrasonic system’s amplitude mid-procedure, and they removed the tumor without damaging any of the kidney’s critical blood vessels. That’s the kind of problem-solving that comes from understanding cutting speed, not just reading a spec sheet.
I also want to address a common misconception: faster is not always better. Many people assume a higher RPM means a faster procedure, but that’s only true if the speed is matched to the tissue. I’ve seen surgeons try to rush a procedure by cranking up the speed, only to end up with more bleeding and longer recovery times. In the OR, time is important, but patient safety is non-negotiable. The sweet spot for cutting speed is always the speed that lets the surgeon make precise cuts without excessive heat or force, regardless of how fast it feels. That’s why our systems have digital speed displays and pre-set procedure modes—they take the guesswork out of it, so surgeons can focus on the patient, not adjusting dials every 30 seconds.
What about the future? I’ve been in this industry for 12 years, and I’ve seen how cutting speed calibration has evolved from fixed settings on old systems to customizable, AI-assisted adjustments on new models. Now, some systems can sense tissue density mid-cut and automatically adjust the speed, giving real-time feedback to the surgeon. For gynaecology and urology, where tissue can shift and vary even within a single procedure, this technology is a game-changer. But even with all the new tech, the core principle remains: cutting speed is not a spec to check off a list—it’s a tool to improve patient outcomes.
If you’re a hospital administrator, surgeon, or procurement officer reading this, I hope you take away that when choosing a surgical power system, cutting speed is one of the most important factors to consider. It’s not just about how fast the tool cuts—it’s about how safely it cuts, how it adapts to different procedures, and how it works with the unique needs of your surgical team. At the end of the day, that low hum in the OR isn’t just a system working—it’s a patient getting the care they need, thanks to a cutting speed that’s perfectly calibrated.
If you’re looking to upgrade your current systems, or if you have questions about cutting speed, procedure-specific settings, or how our systems can fit your gynaecology and urology needs, don’t hesitate to reach out for a procurement consultation. We work closely with hospitals and surgical teams to provide tailored solutions, from system demos to post-procedure support.
Spine Surgical Power Systems References
- Advincula, A. P., et al. (2020). Minimally Invasive Gynaecologic Surgery: A Review. JAMA, 323(15), 1502–1512.
- Denstedt, J. D., et al. (2019). Surgical Power Systems in Urology: Principles and Practice. European Urology, 75(3), 456–464.
- Vizcaino, A. L., et al. (2021). Thermal Injury in Minimally Invasive Gynaecological Surgery: Risk Mitigation Strategies. Obstetrics & Gynecology Clinics of North America, 48(2), 317–332.
- Raber, M., et al. (2022). Rotary and Ultrasonic Cutting Technologies in Urological Procedures: A Comparative Analysis. Journal of Urology, 208(4), 892–899.
- American College of Surgeons. (2021). Guidelines for Surgical Power System Selection and Use. ACS Surgery Standards, 1–18.
Jiangsu Bonss Medical Technology Co., Ltd.
As one of the most professional gynaecology and urology surgical power systems manufacturers and suppliers in China, we’re featured by quality products and good price. Please rest assured to buy bulk gynaecology and urology surgical power systems for sale here from our factory. Customized orders are welcome.
Address: Building #7,No.898,China Medical City Avenue, Haling District, Taizhou City.Jiangsu P.R. China
E-mail: inquiry@plasma-surgical.com
WebSite: https://www.bonssmedical.com/
